Stop 5 of 10
Crown Hair Transplants, and Why They're Harder
Published Jul 31, 2026Sources re-read Sep 22, 2026
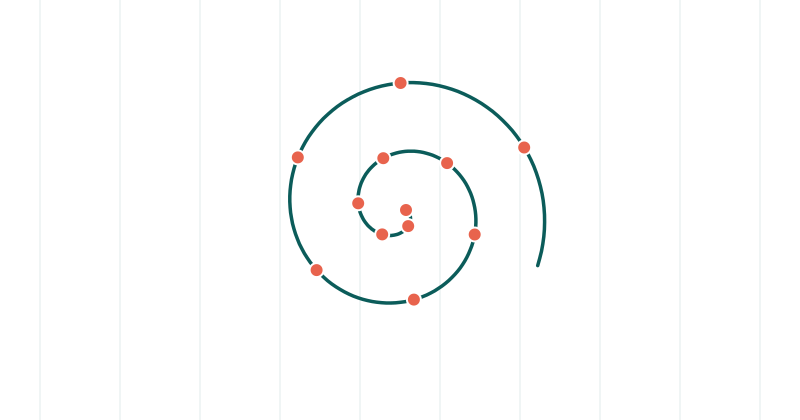
A crown hair transplant is possible, but it is usually harder to do well than a hairline. The crown has a spiral growth pattern that must be recreated graft by graft, it covers a large area that can consume many grafts, and in pattern hair loss it can keep expanding after surgery.
None of that makes crown surgery a bad idea for everyone. It does mean the planning is different, and that some surgeons prefer to wait before treating it. This guide explains why. For the basics of the procedure, see our main guide to the hair transplant: techniques, candidacy and recovery.
What the crown is
The crown, also called the vertex, is the top-back part of the head where the hair grows outward from a swirl. The International Society of Hair Restoration Surgery (ISHRS) glossary defines it as the area at the top and back of the head containing a spiral pattern of hair growth.
In pattern hair loss, the crown often thins as a roughly circular patch that can widen over time and eventually join thinning at the front. People often notice it late, because it is hard to see without a second mirror or a photo.
Schematic. Each stroke is one hair's direction of growth.
Reason one: the swirl
Hair in the crown radiates from a central point in a spiral, called a whorl, and some people have two. To look natural, transplanted hairs must follow that pattern: each incision is angled so the hair points the way the surrounding hair would.
At the front, hair mostly points forward in a fairly consistent direction. In the crown, the direction changes continuously around the centre of the swirl. Getting it wrong is visible: the ISHRS's campaign against surgery by unlicensed technicians lists "wrong hair direction" among the results it sees. Recreating a whorl is careful, time-consuming work, and it is a strong reason to ask who makes the incisions.
Reason two: area and graft budget
The crown can be a large area, and covering it with convincing density can use a great many grafts. Every graft spent on the crown is one not available for the front, and the donor supply is finite.
Surgeons therefore make trade-offs. Many prioritise the hairline and front, which frame the face, and treat the crown only if donor supply allows. Our guide on how many grafts you need explains why these trade-offs exist and why graft numbers are a plan, not a promise.
Reason three: the crown can keep expanding
Pattern hair loss in the crown often continues to progress. A transplant placed into a thinning crown today may end up as an island if the native hair around it keeps thinning.
The American Academy of Dermatology notes that hair loss and thinning can continue after a transplant. The American Society of Plastic Surgeons warns that progressing loss can produce a patchy look and that more surgery may then be needed. In the crown, where loss can widen in every direction, this risk is larger than at a well-planned hairline. This is also why young patients are often advised to wait: the ISHRS notes that the eventual pattern of hair loss is usually not revealed at a young age.
Reason four: it seems slower to show
Crown results can appear to take longer than the front, partly because of how the area is seen. Hair growing outward from a whorl, viewed from above, needs more length and thickness before it looks dense.
General timelines still apply. The American Academy of Dermatology says most patients see results between six and nine months after surgery, and some take 12, while the ISHRS says full results often take a year or more. If you have a crown transplant, expect to judge it at the end of that window rather than the start. Our month-by-month hair transplant timeline sets out each stage.
When a crown transplant can make sense
A crown transplant is more likely to make sense when several conditions line up:
- the diagnosis is pattern hair loss, confirmed by a doctor
- the loss in the crown appears stable rather than rapidly expanding
- the donor area has enough supply for the front and the crown together, now and later
- your expectations are for improved coverage, not the density of your youth
- the native hair around the crown is being addressed, where appropriate, as part of a plan agreed with a prescriber
If several of these are missing, a surgeon may suggest treating the front first, waiting, or managing the crown non-surgically. Whether a medicine is right for you is a decision for a prescriber, not this site.
Technique for the crown
Either FUE or strip harvesting can supply grafts for the crown; the harvest method is chosen for the donor area and your hair, not for the recipient zone. The difference lies in design and placement.
Surgeons plan the whorl's centre and direction, decide how far out to extend coverage, and set a density they can deliver without exhausting the donor area. Our comparison of FUE vs FUT vs DHI explains the harvest choice; placement tools such as implanters or forceps are used in the crown just as elsewhere.
Questions to ask about a crown transplant
- Is my crown loss stable, and how do you know?
- How many grafts would the crown need, and how many would that leave for the front and for later?
- How will you recreate my whorl, and who makes the incisions?
- What happens if the hair around the crown keeps thinning?
- Would you advise waiting, or treating the front first?
A GP or dermatologist can confirm the diagnosis before any of this, and the ISHRS Find a Doctor directory lists member surgeons. Neither pays us anything. The risks covered in our guide to hair transplant side effects apply to the crown as to any area.
Living with a crown that isn't treated
Leaving the crown alone is a legitimate choice, not a failure of planning. Many people are content with a restored front and a thinner crown, particularly as the crown is the part of the head they see least.
If you choose that route, it helps to know that the rest of your plan doesn't depend on it. A conservative hairline, designed with the future in mind, looks natural beside a thinning crown. Treating the native hair with a prescriber's help, or simply revisiting the question in a few years once your pattern is clearer, keeps the donor supply available for whichever area turns out to matter more to you.